Friday, July 19, 2013

"Turn your head and cough, please!" Day 5

Coming to you live from my night shift station. Hopefully my two patients will just sleep through the night and I can get some work done. You just never know how the 8 1/2 hours will go. People do crazy things in the middle of the night sometimes. But let me tell you about my day first.


My posse

Rounds were good and we were just a wee bit late for the morning meeting. Probably the most interesting fact from the meeting was that we had an operation happening today because a penis pump dislocated and was actually protruding out of the skin! Obviously I wanted to see that. But first it was off to the wards to get stuff done.

Job description: Vampire
If you aren't lucky and end up in an elective were the doctors don't care and basically just use you, you will be drawing blood all day. Not that fun but great practice. I am in the fortunate position that I have a really friendly team. Nonetheless we are responsible for the blood drawing. I'm quite happy about it because the practice can't hurt and in my other electives I wasn't allowed to even touch the patient (thank you American hospitals). I like drawing blood. Getting a venous catheter in is another story. I really need my practice in that. Anyways, I was happy when I went to draw blood from a patient and he told me I was going to have a hard time since his veins were so bad and it  worked on the first try. The patient seemed more excited than I was telling me no one had been able to draw blood on the first try in 10 years! Booyah!  
Viktoria 1 : Veins 0

Difficulties while drawing blood: If you have a patient that has veins like me or a young male where you could throw a needle from 10 feet away and still hit, you are lucky and drawing blood is easy peasy. Situations in which it gets difficult,
  • Old granny with basically non existing veins (if this is the case, drawing blood from the femoral vein might have to happen. Big ole needle through the groin area. It looks like it should hurt but some patients prefer it so it can't be all too bad. I've personally never done it.)
  • Darker skin color: People usually like seeing where they are sticking the needle which is difficult with pigmented skin
  • Straight up not visible: This is where I give everyone the advice to feel the veins. The ones you can't see through the skin are often the best ones for drawing blood. You just have to trust your visual thinking. But it works, I promise :)
So, when can I have sex again?
Dr. W and I finished up a few patient letters and set up appointments before heading to outpatient care since they were quite busy. Apparently everyone wants to see the urologist before the weekend. A summary of the cases:


look! My outfit goes well with the outpatient floors
  • A man wanting a circumcision because of foreskin tightness. (Dr.W kind of dissed the American's saying if the patient had been born there he wouldn't have this problem since most boys are circumcised without being asked if that's what they want. Can't say I've heard a single guy complain about missing his foreskin but hey, to each his own. The patient responded by saying he wouldn't have minded being born there. I was afraid it was going to turn into a ethical debate.)
  • A man came in and we had no idea why he was there or who had sent him. He wasn't able to communicate with us either. Perfect. We took a look around and I did an ultrasound of his bladder, prostate and kidneys. We couldn't find anything suspicious accept that his penis was a bit smaller than average which would point towards a low testosterone level. We ended up finding out that he was supposed to be transported to his urologist in town for a shot against prostate cancer. This would explain our findings. Prostate cancer patients are given anti-androgens which lower the testosterone level.
  • A woman with bloody urine (I had to go to the OR in the middle of taking care of this patient so I don't actually know why her urine was bloody or what they ended up doing.)
  • An ileum conduitoscopy was performed. An ileum conduit is another form of replacing a bladder in contrast to the neobladder I wrote about yesterday. A piece of small intestine is attached to the outer stomach and is open to the environment. A bag it placed over the opening to collect the urine. The ureters are attached to the ileum conduit on the inside of the body. It looked a bit bizarre from the outside. Anyways, the patient also had bloody urine flowing so the attending took an endoscope to look around.
  • A check up appointment with a young male after circumcision. His main question was when he could start having sex again. His girlfriend was getting ansy after 2.5 months. Oh teenagers...
What is the patient's feeding tube doing?
I headed into the OR to see the second half of the implant removal. I arrived in the OR at the point where they had already removed half of the pump and where working on the other half. It's rather interesting to see how a little pump is implanted into the scrotum and the inflatable tube in the shaft. I just imagine it being too funny to pump up an erection by squeezing the scrotum. But hey....its the result that counts, right? How you get there isn't that important ;) After they had removed the whole pump system (since it was badly infected and the patient wasn't going to need its function anymore anyways we didn't implant a new one), he was given a suprapubic catheter, (The bladder is filled with fluid and then a big needle is poked through the lower stomach to the bladder and urine flows over a tube into a bag.) and sewn up.


All green everywhere


Dr.H is too funny. I was standing by the patient's head with two nurse students watching the operation. Dr.H was holding on to the tube that ran from the scrotum to the penis. As he pulled on it, trying to remove it, he asked us if the patient's feeding tube was moving in further. We three quickly checked to see what the feeding tube was doing not realizing that he was totally messing with us. Lol. It was funny to see how quickly we just obey without thinking about why. He got us.
Dr.H 1 : Students 0 
I really think I'll like working in Urology if those are the kind of guys I'm working with.


I told you it's bad! No really....it's bad!
Back on the ward I was supposed to write a patient release letter. I told Dr.W my German grammar was horrendous and that it would take me some time to get the wording down. He came back so fast though that I had just gotten my rough draft ready (very very rough). He said it couldn't be all too bad and read it. I really didn't want him to knowing exactly that would happen which did. He was completely amazed just how bad it was. He thought I was just kidding. He was quite amused (as are my relatives and friends by my grammar as well.) Of course I don't like not being good at something but honestly people, my German grammar lessons are limited to 4th and 6th grade. I let the people laugh and have their fun and tell them they should speak English or write me a letter and then we will see who's laughing. Being bilingual is a gift but also makes life difficult sometimes because I mix up things from both languages without noticing. A lot of the time my friends will notice and laugh about it secretly or tell me months later after letting me go through life thinking I was saying it right or, if you are like my aunt, will have a good hard laugh at what I said and then tell me and proceed to tell the rest of the family. Dr.W was amazed because he said he doesn't notice anything when I speak to him. I said I just needed to read a lot of release letters to get a gist of the wording and then it wouldn't be a problem. But there is no way I am taking German grammar classes additionally to all the other stuff I have to do. It's just something I will have to work on to avoid another situation like today.

Where is everybody at?!
After that incident, I headed over to the lab to get my reactions from yesterday done. Except for the Professor, no one else seemed to be in the building. It was only 3:30pm. Guess they all left early for the weekend. After 1 1/2 hours I was done and headed home to nap before coming here.

So far my patients are sleeping. Lets hope it stays that way!

Baci, V

Thursday, July 18, 2013

"Turn your head and cough, please!" Day 4-ever long

Today was a busy day. Started at 6AM and ended at 6PM.

Rounds were completed early today. Booyah. After the morning meeting I talked to the chief because I wanted in on his operation. A Neobladder. I'll explain below. He said he'd page Dr.W when it was time for me to head into the OR. Very friendly man.

WWVD: What would Viktoria do?
It was very important to me to check on the patient that wanted to talk to the pastor yesterday to make sure the nurses had arranged that. Just for the case that they didn't, I took a picture of the flyer and realized that there were two numbers. One if I needed someone evangelic and one for the Catholics. I had to draw her blood anyways so I decided to get all my questions asked. She informed me that there hadn't been anyone religious to see her yesterday but that her daughter had stopped by. I asked her what religion she was so that I could personally call and get a meeting organized since the nurses had failed me in that aspect. I told the patient that I hadn't forgot about her and was on ward personally 4 times yesterday and reminded the nurses that that needed to get done. As soon as the other patients' blood was drawn I called the number. I only got the answering machine but left a message with all the important infos for someone to find my patient. (I stopped by at the end of my day to see if anything had happened. The patients daughter happened to be visiting so I was able to introduce myself to her. I was very happy to see the patient in much better spirits and happy to hear that the pastor had stopped by, he was a very nice man and was coming back tomorrow. Sometime you have to take things into your own hands to get stuff done.)

Neobladder
I was paged into the OR and had luckily completed all my other tasks in time to head down and get changed.

A tip for anybody who plans on being in the same situation as me. When you get into an operating room. Say hi and explain your function. You can only see the peoples eyes and stature so you aren't always recognizable and these people work as a team day in and day out. You are invading. So introduce yourself at the beginning and thank them for their help at the end. It will make your life easier.

I got myself scrubbed in and had the OR nurses help me get dressed. The chief and one of the attendings were the main operators and I got to assist. They were currently removing the patients bladder. This patient had an advanced bladder cancer which is treated surgically by removing the bladder and in the case of a male, the prostate as well. The chief explained a bit to me and also asked me a bit about the anatomy we were seeing.

I luckily didn't have major circulatory issues. That is in part because I've been on my feet the last three days and secondly certainly because of these hot anti-thrombotic socks (I call them med-Spanx). Patients wear them so they don't get a thrombosis from standing, medical personal wears them to keep the blood in the upper body while having to stand for longer periods of time. Life savers.


Another tip, if you are standing or on your feet for a long time and aren't used to it yet, definitely get yourself a pair from the ward. It can help you avoid embarrassing (but also normal) falling over in the OR.

Once the bladder was out, the cool part happened. A part of the small intestine was removed, the other parts of the small intestine just reattached to each other. With the part of the small intestine used to make the new bladder the following was done.
  • The tubular intestine was cut through from one end to the other to have a long narrow sheet of intestine wall if you will.
  • This sheet was formed into a W and sewn together. So the long narrow sheet turned into a more rectangular/square piece of intestine. 
  • The two ends were sewn together to a ball
  • The ureters were attached to the top and the urethra to the bottom
  • Voila! A new bladder
  • If you can't quite picture what I mean (and I'd totally understand) just google neobladder and look at images and you'll get the idea.
It obviously doesn't completely work like a regular bladder but it keeps the people continent with a few things to watch out for on a daily basis.

I could live off its contents for at least a day.

My lab coat. My portable locker and cafeteria. My survival kit. My entertainment.
Thought I'd give you an insight into all of this and all the things I carry around with me.
In the picture:


Top left: 4 pens (the doctors keep stealing mine so I stock up) / 2 highlights for important notes that shouldn't be missed / flash light for pupil exams / mini notebook containing notes, numbers, cash and coffee card / I.D. so I can buy food (if money is on the dang thing) / iPhone (duh!)

Bottom left: Urology book / lab cheat sheet / granola bar / Tums

Bottom right: Stethoscope / water bottle (not pictured, just finished) / keys / alternative iPhone location

It's a bit of weight I carry around but it gets me through the day.

I grind because I want that doctor title

In Germany, you have to do a doctor thesis in order to call yourself Dr. Hasselhof. Otherwise I would just be Mrs. Hasselhof. I want that title. So after the OR and checking up on my patients again, I headed to the lab for 3 hours to get a bit more work done. Not gonna lie, while waiting for my last reaction to finish up, I took a 15 minute nap at my desk. I was exhausted.

Tomorrow I am hoping to get out a bit early to get some hours of sleep in before my night shift starts. We shall see how well that works.

Baci, V


Wednesday, July 17, 2013

"Turn your head and cough, please!" Day 3

Today was a busy day. I was so exhausted I had to take a 2 hour nap after work.

It's not even because I was so busy with patients per se but Dr.W and I are responsible for the patients on the half ward on the 5th floor and the urological patients on the 7th floor on the OBYGN/URO ward. Additionally we helped out in the clinic today (2nd floor and in the main building) and Dr.W is an avid smoker (tsk tsk tsk) which meant about 5 smoking breaks on the other side of the building on the main floor. We were constantly going from one place to the other. I should really wear a pedometer. I'm sure I got a lot of miles in today. In addition, my muscle soreness from Yoga yesterday started to kick in.

Anyways, as always up bright and early. Rounds were fine as was the morning meeting. Dr. W and I took care of business on the ward; blood drawn here, paper work done there, tried to get in touch with other doctors. It's amazing how much time is spent on not primarily medical procedures. We had to find an internal medicine doctor for one of your patients and it probably took half a day until the responsible one was found and actually showed up! Then it was a crazy mix of running all over the place and getting various things done. No lunch was had. I survived off of a granola bar and two chocolate milks that I grabbed off the ward and a little pack of gummi bears that the nurses gave me. Dr. W seemed fine with his coffee and cigarettes. Told him he was on a cliche model diet :)

Here some highlights of the day:

Honestly one of the best feelings in the world.
We were able to tell a patient who had a very large kidney mass (which in 90% of the cases is cancer) that she fell under these 10% and didn't have cancer. She immediately jumped up, hugged Dr. W and teared up. It was an indescribable feeling to know what joyful news you are about to give a patient. It's like waiting for someone to open a present because you know how happy they will be.

Would you like to talk to someone?
Obviously doctors don't have all the time in the world to constantly talk to patients. I think the average time a patient sees a doctor is about 3 mins. Nonetheless, a lot of doctors just aren't compassionate enough to care (which baffles me when they picked this job but apparently they still only see the disease and not the patient). One of our patients really had a lot happen to her. She has a feeding tube, can't keep anything in her system, came for one thing but there is always something that is keeping her from leaving. In addition, she has an infection which requires her to be alone in a room and for us to always come in with protective wear and face masks. I usually don't go into the isolation rooms during rounds to save on clothing but I did over hear her saying she wanted to talk to a therapist which the attending either decided to ignore or didn't understand that she meant a psychologist and not a normal doctor. When I went to draw blood she told me she felt like giving up. That is something you never want to hear from people. It just sad. So I talked to her a bit and realized A) how much she appreciated my time but also B) that I wasn't enough and also didn't have all day. I told her I would talk to the nurses and have them get a psychologist or even better a pastor or religious figure to come talk to her. She told me that would be so great because she just needed support in this hard time. So I did just that. Asked about 3 more times during the day if that person had finally shown up and finally the late shift nurse said that she would get on it. Next time I see a case like this again I will call the hospital pastor myself. I didn't want to overstep my position and go behind the nurses backs because as I said earlier, you want them to be your friends. Long story short, a little bit of my time can back a big difference in a patients life. A little compassion never hurts.

Coming to you live from the patients bladder!
We performed a cystoscopy (looking at the bladder) on one of our outpatient patients. It was very interesting to see the bladder live and in color. Usually men aren't a big fan of the exam because well,....a camera is inserted through the penis. I personally can not comment on the painfulness or unpleasantness of this procedure but welcome you men to imagine what that might be like. Don't worry, they get a numbing gel inserted first....we aren't that cruel ;)

You don't puncture the amniotic sack when the baby is coming!
Oh lordy lord. One of our outpatients was interesting and complicated to say the least. The whole time she told us things I just wanted to give her an anatomy book. Let's just say I don't think she was aware that there is a seperation of the the urethra and bladder to the vagina and uterus. Her theories were quite absurd as were her reasonings. Just as a little taste, we needed to get catheter urine from her and she told us she had to pee first since the bladder was full. When we told her that was good because we needed a urine sample (which btw she wanted to give us, we didn't really need it) she said that doesn't work because the urine is already on its way (I don't think she is aware that there is only a very small distance the urine can go from the bladder as a women, men have a few more cenimeters, so if its "on the way" its actually already out) and that you wouldn't puncture the amniotic sack if the baby is on its way. Yeah......no sense what so ever.

It was a full day but that's good. Saw a lot of patients got a lot done. Tomorrow I am hoping to help with a pretty interesting operation. Come back tomorrow to find out more :)

Baci, V


Tuesday, July 16, 2013

"Turn your head and cough, please!" Day 2

Today really was a day of standing around and waiting for something to happen.

Once again I started off on the ward at 7AM for rounds. This time we actually got through them on time. The morning meeting was a nice and relaxed atmosphere (I've sat in way worse). We were done by 8 and had a 15 minute break before we had to attend an hour long hygiene seminar.

I thought it was being held by a hygiene person from the hospital so I removed all my jewelery just in case. It turned out to be a seminar by one of the attendings responsible for hygiene in the department so I probably could have skipped taking out my nose ring. Oh well. (they are actually allowed, FYI, but I didn't know how picky the person might end up being).

Once again there wasn't much happening on the ward. I was however given the task of measuring the residual urine of one of our patients. This ultrasound is done after the patient pees to see how much urine stays in the bladder (large amounts of residual urine are the perfect growing grounds for bacteria and can lead to urinary tract infections which can be dangerous in men with all the anatomical structures hanging out around the bladder.) My patient was just fine though.

With no more tasks to perform on the ward I headed down to the clinic. The OR only had two operations happening. The varicocele operation unfortunately didn't take place. The other one was a one-man-job and the last was a renal gland removal and all the good spots where taken by residents :( Luckily, smaller operations where being performed in the outpatient department and I was able to watch a ureteric stent being inserted and a kidney stone removal. The stone was too big to pull out whole so the doctor had to break it up before removing it. It looked like a fun operation to perform. (breaking things for a good cause is always fun!) And here a sneak peak at the radiological version of a statement necklace:


There weren't very many patients for us electives to examine but any eligible patient had to deal with us first. I took a few histories and even did the kidney and bladder ultrasounds, printed out the pictures and discussed my findings with the doctor. I was quite proud of myself that the ultrasound pictures turned out so nice.

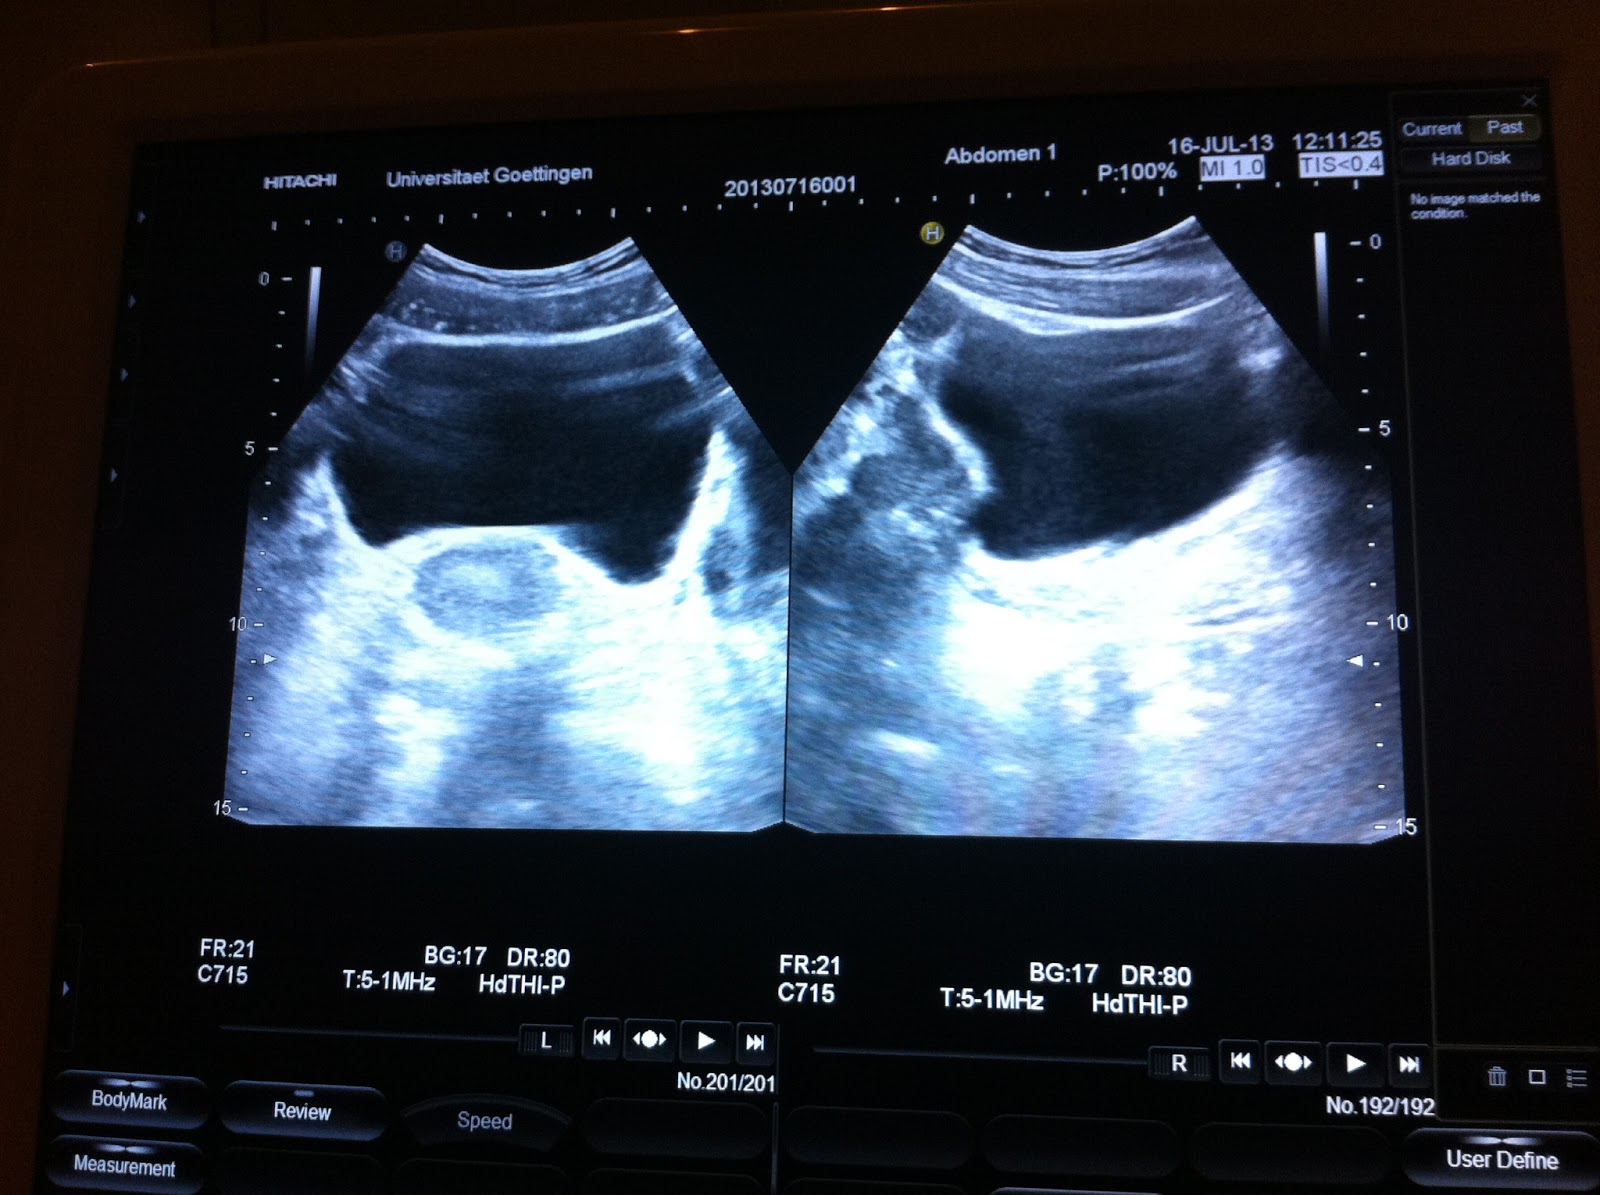
Since I hate standing around doing nothing (especially when I have a million and one other things that need to be done) I was constantly looking for work to do, reading files and even organized a room for us electives to practice ultrasound on each other. I present to you, my bladder:


After a few hours I headed back up to the ward to see if anything could be done. Sadly nothing. So I decided to go to the lab and at least get a bit of work done on my doctor thesis.

I am not giving up hope that it won't get more exciting the more I know. My plan is to be really aggressive with the doctors and force them to let me do things or explain things to me. I've got some papers to read packed for tomorrow just in case.

Hopefully I'll have better stories to tell tomorrow. Sorry :/

Baci, V

Monday, July 15, 2013

"Turn your head and cough, please" Dia uno

"Since when do you speak Spanish, Viktoria?" I really don't but we'll get to that.

6:15AM
Getting up at 6:15 is just a bit early for my liking. Thankfully its bright out by 4AM otherwise getting up would be so much worse. I just kept telling myself its actually around 10 and time to get to the hospital. My body was not ready for breakfast though. I did force myself to eat a not so fresh banana though and headed over.

6:45AM
I got my lab coat filled up with books, stethoscope, notepads, iPhone and gum and headed to the ward. I was a bit early so I took the time to introduce myself to the nurses. Note to any med student: They can be your best friends or worst enemies but its ALWAYS good to have them on your side so try real hard so that they like you ;) One after another the doctors started showing up. Mostly guys, no surprise (2 of the 3 female doctors are at home with their new babies). In addition to myself, there are two more girls doing an elective in the department and a female intern (where are all the future male urologists at?). I decided to stick on the ward the first day to see what patients we have currently in treatment.

7:05AM
Dr.W, Dr.H and I did rounds on the two wards not part of the main ward. Nothing exciting to tell from that really. Since Dr.W had been on vacation the last 7 weeks and Dr.H just recently came to the department and the department recently got a new chief, my two doctors weren't quite sure when the morning meeting was taking place. They guessed 8AM. We didn't get through rounds and to the room until 8:12. We thought we were really cool because we were the first ones there. After about 2 minutes the chief walks in and tells us how cute we are sitting there because the meeting ended at about 8AM.....because it starts at 7:45. Oops.

8:15AM
Dr.W, an elective and I headed back to the ward and we discussed our current patients, treatment options, complications and further planning. Since it was a Monday, there wasn't a lot that needed to be done. The elective and I headed to the clinic to see if we could help out there.

9:00AM-1:45PM
Dr.M was in charge of the admissions for the day. We were allowed to head in and chat with the patients and get their history before he would join us, look over everything, discuss the upcoming procedures, get consent and send the patients up to the ward. We were in charge of getting their blood drawn and getting urine samples.

The four patients I worked with already nicely showed the variation in patients that show up in urology. Our youngest patient (already on the ward) was in his late 20s while the oldest one admitted by us today was a 81 year old female.

The cases included testicular cancer, kidney stones, varicoceles, kidney cancer and obstructions. We even ended up doing ultrasounds on the patients. I saw a patient with double kidneys on both sides, kind of bizarre! So although I wasn't in the OR today, it was a relaxed and informative day.

I'm always happy when I can use my English speaking abilities to help out in Germany. So when they told me the next patient only spoke English and Spanish I was excited and so where the nurses and doctors that I was there. Gosh dang it, why didn't I learn more from Mr.Wannicke back in High School?! I quickly looked up some Spanish words in case I'd need them. The standard: el testiculo, la vena, la arteria, los cojones (which is actually vulgar and was obviously not used with the patient) and so on because I was basically working with: si claro!, una cerveza por favor and vamos a la playa (all irrelevant for my case). Luckily the patient spoke English well enough that we could stick with that. We got all the work up done and then Dr.M joined us. Out of no where Dr.M starts speaking Spanish with the patient! I was flabbergasted! It wasn't fluent but it was a heck of a lot more than I had expected to hear out of his mouth! So with English, Spanish, German and hands and feet we explained the upcoming procedure to him and answered his questions. I even understood their conversation which just shows you that any little amount of foreign language can help out in unexpected situations! Stay in school and pay attention kids ;-)

After that I had to accompany my friend PKay to the ophthalmologist in Hannover so I had to leave early.

The other electives and I decided to split up the departments clinic, ward and OR amongst ourselves during the weeks and rotate weekly or drop in and help if our respective department was running slow. I said I'd continue ward since I had started there this morning which unfortunately means being on ward every morning at 7 for rounds but since they are experiencing a bit of a summer break, I will try to get into the OR tomorrow as well.

On a side note: A thing I deal with basically every first day of an elective is my circulatory system. After months of just sitting in lecture to then sitting at my desk my body is not a fan of having to suddenly stand all day. Thus, the first few hours of my day are a roller coaster of feelings. Either I feel great or feel like I'm about to faint and no amount of water or pumping my muscles while standing can change it. I'll probably have the same phenomenon in the OR tomorrow with bright lights, multiple layers of clothing and face masks that make me think I'm getting less air.

It's an absolutely terrible few hours but after that I am good to go for the rest of the time. Basically I just want to make everyone aware of the fact that this is a completely normal thing! Most people are embarrassed by it and stand in the OR trying to keep it cool and the next second they are lying on the floor. No fun for anyone especially if there is a patient on the table because honestly that person is more important than your dumb ass that didn't just say you need to sit down a second. I've had doctors from all levels insure me that it is totally normal and nothing to be ashamed of. Just thought I'd share that with y'all :)

And now for your urological entertainment. Meet the waving Eskimo.
We discovered him in our second semester during anatomy and in all reality he is actually a penis with cut open scrotum....you are welcome.


I'm off to bed, I'm spent.

Baci, V

Sunday, July 14, 2013

"Turn your head and cough, please!"

I'm back baby! In the mean time I have completed my fourth year of med school (craaaazzzy!). Tomorrow I start my month long elective in, wait for it......Urology! (thus the new title of this one month long adventure). Now most people's first reaction is, "Ewwww, WHY?!?!?". But I say, " Why not?!"

In theory, Urology might turn out to be the best specialty for me. This month will determine if that all holds in practice too. It's not just about testicular exams, prostate checks and incontinence. Those just seem to be the things most people associate urology with (all very important, nonetheless).

But seriously Viktoria, why? you might ask. Well here is why:

  • It's a small surgical field.
    • Surgery has always been my dream and goal but after a month of plastics, I just realized I don't exclusively want to be standing in the OR every hour, every day. I like the detective work of internal medicine as well and Urology combines both quite nicely.
  • It has about 70% male, 30% female and children patients
    • I really like OBGYN because of the deliveries and elegant operations but lez-be-honest people. I'm a tomboy on the inside. Grew up with a bunch of guy friends, need them, love them, can't live without them. So the thought of working in OBGYN were you exclusively have female patients (unless the baby being born is a boy), the nurses are mostly female and in today's day and age, the doctors are mostly female. TOO MUCH ESTROGEN! In Urology I will still see some woman and maybe even their babies if they have urological problems after delivery. I can also specialize even further into children's urology.
  • No middle-of-the-night calls into the OR (well almost none)
    • My Urology professor told us that there are only two emergencies in Urology, everything else can wait. I do plan on having kids one day and I really like my sleep so if this turns out to be the case, it works for me :)
  • Death is not very present
    • I know I could deal with the deaths of my patients but it is nice if you can help without death being a regular outcome. Of course fatal diseases exist in the field of urology but in comparison to other fields (Oncology, Cardiology, etc.) its not as present. The patients often have a lot of pain (have you ever had a UTI....no fun right?) but the treatment options are good and you can really help the people.
  • I can be sassy
    • I'm the type of girl that doesn't really care what you think and have a pretty tough skin (especially after having been in the modeling scene). Consequently, if a patient feels uncomfortable (Men really are the worst patients, such wussies ;) ) having a female doctor and feels the need to make a snipe remark, you better believe I've got a reply. So if they start complaining that a prostate exam might be uncomfortable, I've got the personal experience of a OBGYN examination and can tell them to calm down because in comparison to what we go through regularly, this ain't nothin!
  • Best jokes at a party
    • I will be dealing with penises almost all day....you KNOW there are going to be good jokes to tell at parties. The things people do sometimes. I will only say: vacuum cleaner accidents, auto-erotic accidents and fractured penises (although there is no bone, it can happen).
  • I will help people to have a better sex life.
    • 'Nuff said
So starting tomorrow at 7AM we will see if these points hold. If the next four weeks go well and I like it, this will most likely be my specialty. But let's convene at the end of it all and see where I stand.

My plan is to post throughout the whole experience, either at night or during breaks from my iPhone. Obviously I am fully aware of the patient confidentiality law which I fall under so you won't see names or any details that might reveal the identity of my patients but I will give you an insight into my day and will hopefully have fun stories and accomplishments to share.

So please enjoy!

Baci, V

Thursday, September 15, 2011

Vorklinik is officially OVER!

Hey Everyone! Its over! Has been for about 2 weeks now. The end result was amazing. The last few weeks of MediLearn just started being daily life. I got so used to working all day. Once the whole thing was over and the day came to write the exam...I felt nothing! Absolutely no adrenaline. None. I went in there and just worked my way through the 160 questions. I didn't even really have a different feeling going out of it which kind of upset me. I had hoped that the adrenaline would have kicked in because I feel that this is a vital part of such an important exam. On the other hand, I had been studying my butt off the past few months and I had the feeling that I was prepared. Of course I didn't know everything but you can't study for every last protein or enzyme there is. We were able to put our results in on the internet and the results were compared to the answers of all the other students that added their results giving us an estimation of what our score could be. As the day went on, MediLearn posted their answers. For the first day I most likely have a 2 (equaling a B) which was what I wanted. The second day wasn't any different on the adrenaline level. However, I was done after about 1.5 hours and spent the rest of the time drawing. I could have left but then I would have had to give up my answer sheet and pick it up later again. Since I wanted to wait for my friend anyways and wasn't going to start studying anymore on that day I had nothing better to do. I went home after the exam and put my answers in the internet. Again, most likely a 2! I was so bored and didn't know what to do with myself and was very happy when a friend of mine asked if I wanted to go to the pool with him. It was nice laying in the sun for a while.
The next week consisted of studying for the oral exam giving each subject two days. The day of the oral my adrenaline gland finally decided to do something. We got our histology glass plates and got to look at it under the microscope for 15 minutes. The next 4 hours was just sitting there and waiting to be asked. Since I was the first one to be asked I always had an hour between the subjects. They usually were quick hours because I was waiting for the next subject but once I was all done I had to sit through another hour which took forever. End result....1..!!!! We were a bit shocked when they told us but overly happy. To be fair, they did ask some really tough questions (even admitting that themselves) but we also rocked it. 
The next day I was cleaning and packing and then the next day I was on my way to my grandmas house so I never had a minute to just breathe. The next morning I flew home with a friend and spent the last 10 days shoving America down her throat. Today was my first day since the monster that is Physikum is over. In the end it wasn't a big deal. If the rules that I have heard are true my final score will be a 1 (=A) which would be fabulous. Now I am going to sit back and relax for the next few weeks doing things I like to do :)